Two of the leads in my inbox this week came from healthcare. One was a Sydney allied health group running four physio and chiro clinics. The other was a national disability services provider with around 150 staff across three states. Both knew AI could save the practice 10 hours a week, and nobody had told them in plain English what the law requires.
I run client success at Aivy, an AI automation agency in Melbourne. Most of the clinics we work with have already tried Heidi or Lyrebird, and many quietly walked away the moment someone mentioned the Privacy Act. The 10 December 2026 deadline turned that nervousness into a real procurement question, and the regulator is no longer in education mode: its first compliance sweep began in January.
This guide walks through what changes in December, what AHPRA expects from you personally, and which AI tools actually belong in an Australian practice. It is organised by clinic type, so a GP partner, an allied health owner, a specialist and an NDIS quality lead can each jump straight to the section that matters, then finish with a 90 day rollout plan.

What changes for Australian clinics in December 2026
From 10 December 2026, a clinic whose software uses personal information to make, or substantially help make, a decision that significantly affects a patient must say so in its privacy policy: the kinds of information used and the kinds of decisions involved. That catches AI triage, AI rostering and clinical automated decision making; scribes that only draft notes are greyer, and worth disclosing anyway.
Health service providers do not get the small business exemption that other sectors enjoy. The Privacy Act applies to your clinic no matter how small your turnover. If you bulk bill Medicare and you use a scribe, the rules apply to you. Clinics tendering for public health work are usually measured against the ASD Essential Eight baseline as well.
The new rules come from the Privacy and Other Legislation Amendment Act 2024. The OAIC published its final guidelines on them on 30 September 2026 and is already enforcing: its first compliance sweep, from January 2026, covers around 60 organisations across health, property and other sectors. Penalties for a non compliant privacy policy reach $66,000 per breach.
Source: Privacy Act 1988 and Privacy and Other Legislation Amendment Act 2024.
- Our recommendation: have the updated privacy policy live by 1 November 2026, which gives you a five week buffer before the deadline.
- The full mechanics: for the rules in detail and a decision tree for using ChatGPT or Claude with patient data, see our Privacy Act AI compliance playbook for Australian businesses. The rest of this article focuses on which AI tools survive the deadline, by clinic type.

Four questions to ask any AI vendor in healthcare
Before you pick a tool, ask every vendor four questions. Most healthcare AI contracts I review skip them, even though they decide whether the tool survives 10 December or becomes a compliance liability. We put another sector through the same interrogation and published the vendor claims we checked line by line for trade software, which shows how much a demo leaves out.
Vendor decks lead with accuracy numbers and time saved per consult. They rarely lead with where your patient audio is stored, who is accountable when the AI is wrong, and whether the tool maps to the Medicare items you bill. Asking those questions before you sign is the point of independent AI consulting for clinics, because no vendor volunteers the answers.
- Where is the patient audio processed and stored, and which other companies see that data on the way through?
- Who is accountable when the AI is wrong: you the practitioner, or the vendor? Almost always the answer is you.
- Which Medicare item numbers or NDIS standards does the tool template against?
- How do you delete every patient record from the vendor’s systems in 24 hours if a breach happens?
Sources: AHPRA professional obligations guidance and RACGP AI scribes fact sheet.
If the vendor cannot answer any of these clearly and in writing, that is your answer. Move on. Australian clinics that did this during procurement deployed in weeks; the ones that skipped it spent months untangling contracts after the OAIC started asking questions. To score where your practice sits, our AI readiness assessment walks you through it.

Best AI medical scribes for Australian GP clinics
If you run a GP clinic in Australia, the real choice for an AI medical scribe is between Heidi Health and Lyrebird Health. Both are Australian, both store your data in Australia, and both pass the privacy checks. The deciding factor is your practice management system: Lyrebird is now free for every Best Practice Premier customer through an official partnership.
That puts a credible AI scribe within reach of roughly 85 per cent of Australian GP clinics at no extra cost, so on BP Premier it is the default. The scribe is rarely the biggest line on a clinic software bill, though. We normalised what Cliniko, Halaxy and Nookal actually charge per practitioner, and that spread is wider than any scribe subscription.
Sources: Best Practice Software and Lyrebird Health × Best Practice partnership.
- On MedicalDirector: the easiest path is Telstra Health Smart Scribe, which lets you pick Heidi or IntelliTek as the engine. Heidi is generally the stronger choice if you bill complex Health Assessments (MBS items 701, 703, 705, 707) or GP Chronic Condition Management Plans (items 965 and 967, which replaced 721 and 723 in July 2025).
- Heidi’s credentials: the only Australian scribe with ISO 27001 security certification, used at scale by Monash Health and the Queensland Children’s Hospital. Be cautious of vendor claims of huge documentation time savings; the peer reviewed evidence is still early.
| Tool | AU host | Price | PMS native | Privacy ready |
|---|---|---|---|---|
| Heidi Health | Yes | ~$150/mo | BP, Gentu, Halaxy, MD | Yes (ISO 27001) |
| Lyrebird Health | Yes | Free (BP) or $2,400/yr | BP, Genie, Gentu | Yes |
| Telstra Smart Scribe | Yes | Tiered | MedicalDirector | Yes |
| PatientNotes.ai | Yes | $80 to $110/mo | Cliniko, Halaxy, Nookal | Yes (MBS templates) |
| Medow Health | Yes | $150 to $200/mo | Gentu (specialist) | Yes |
| i scribe | Yes (Sydney) | Subscription | Gentu | Yes |
| TeleScribe | Yes | $69/mo | Clipboard | Yes |
| Halaxy AI | Yes | Inside Halaxy | Halaxy native | Yes |
The honest answer for a GP partner in 2026 is this. If you do nothing else this year, turn on Lyrebird Free inside BP Premier, write a 200 word AI scribe policy, and send it to your indemnity insurer. That is the cheapest compliant stack on the market for a Melbourne clinic looking at AI automation.
AI scribes for Australian specialists and Gentu users
GPs are the easier case. Specialist consults run longer and produce more clinical nuance than a 15 minute GP appointment, so the scribes that handle them well have speciality templates and configurable output. For specialists running Gentu, the practice management system from Magentus, Medow Health and Heidi are the usual choices; both integrate deeply and store data in Australia.
Medow Health is built for specialist workflows, with templates for cardiology, dermatology, paediatrics, oncology, urology and more, at around $150 to $200 per practitioner per month through Magentus. Heidi trades some speciality depth for ISO 27001 certification. The choice comes down to whether registrars need rigid templates, or senior consultants want to dictate freely.
Sources: Magentus marketplace and AU specialist scribe pricing 2026.
- Not on Gentu: i scribe is worth a look. It runs on Sydney servers and integrates with several systems through its API.
- Smaller vendors: AISA, TeleScribe and MEDILIT all run on Australian cloud infrastructure and suit small specialist practices wanting a low cost option.
If your model depends on long initial consults and detailed letters back to GPs, pay for speciality templating: the uplift from a properly captured 45 minute item easily covers a $200 per month scribe.

AI tools for Australian allied health practices
Allied health has it easier than specialists. Cliniko, the dominant practice management system for physios, occupational therapists, podiatrists and many other disciplines, has an open marketplace that plugs a scribe like Heidi or PatientNotes straight in, and the same is true for mental health practices on Power Diary, now Zanda Health. The Australian Physiotherapy Association calls AI a collaborative tool, not a replacement.
- Physio and OT: Cliniko plus Heidi or PatientNotes, both Australian and both privacy ready.
- Medicare and DVA billing: PracSuite is a strong alternative if billing is the bottleneck, because its billing automation is generally faster.
- Psychology and mental health: Power Diary plus PatientNotes is the most common combination, because PatientNotes ships templates for Mental Health Treatment Plans (items 2700 to 2717) and Better Access initiative items.
One caveat for mental health. The Australian Psychological Society warned in 2026 that patients are at risk from AI mental health services rolling out without proper evaluation. Consent for AI in a mental health consult needs to be explicit, documented and revocable; do not assume the general privacy policy covers it, especially for clients with trauma histories, and run the conversation before recording starts.
The verdict for allied health: the practical stack is Cliniko plus Heidi or PatientNotes for physio and OT, and Power Diary plus PatientNotes for psychology and mental health. For mental health work, patient consent for AI needs to be explicit, documented and revocable, so run the consent conversation before the recording starts.
AI tools for Australian NDIS providers in 2026
NDIS is the highest stakes AI conversation in Australian healthcare right now. The 2026 pricing reset and the NDIS Commission’s tougher audit posture make AI tooling a margin question, not a productivity nice to have. The right AI for rostering and evidence collection can be the difference between passing an NDIS audit and losing your registration; the wrong one can do the opposite.
Sources: ShiftCare and Lumary product documentation; NDIS Commission audit standards.
- Under 50 staff: ShiftCare is the most widely adopted tool in Australia. It predicts participant demand, flags rostering conflicts, generates GPS stamped progress notes and submits NDIA claims natively with no per claim fee, and providers report 15 to 25 per cent faster schedule creation. Rostering platforms are priced very differently from clinical software, and what they actually cost per user is worth checking first.
- Over 50 staff: Lumary becomes the more credible choice. It runs on Salesforce, handles aged care and allied health alongside disability, and gives compliance teams the audit trail they need. If you are weighing a packaged platform against something built around your own workflows, our guide on whether to build or buy a clinic platform in Australia works through the trade offs.
| Tool | Best size | Rostering AI | NDIA claiming | Practice Standards |
|---|---|---|---|---|
| Lumary | 50+ staff | Yes (Salesforce AI) | Bulk | Yes (deep) |
| ShiftCare | Under 50 | Yes (demand prediction) | Native, free claiming | Yes |
| SupportAbility | 20 to 200 staff | Workflow automation | Yes | Yes (audit grade) |
| Brevity Care | Small | Basic | Yes | Standard |
SupportAbility is the third name worth knowing if compliance is your bottleneck, because it attaches NDIS Practice Standards directly to participant records. The Commission now assesses on evidence, so AI used for rostering, incidents and restrictive practices needs a documented trail of where participant data sits. For NDIS tooling and compliance, see our NDIS AI compliance specialists page.
When your AI tool sends patient data overseas
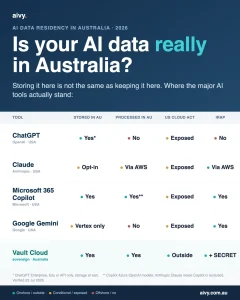
One question applies equally to every clinic, GP through NDIS: where does the data actually go? The audio of an AI scribe consult usually streams through a speech to text service, then a large language model from Anthropic, OpenAI or Google, then back to the vendor for formatting, and where each provider stores your data depends on rules like the US CLOUD Act.
Each of those steps can be in a different country, and under the Privacy Act your clinic remains accountable for how the overseas company handles that information. Most clinics do not have the paperwork to prove they checked. The same offshore question now applies to identity checks: when a flagged Claude user verifies, where your face data goes is a US vendor.
- Stored overseas: Suki AI, Lindy.ai Medical Scribe, Abridge, Tali AI, Microsoft Dragon Copilot and Doximity Scribe all store data in the US or Canada. Several are marketed in Australian app stores, which makes it easy to assume they are compliant. They are not necessarily non compliant, but they need a documented privacy check most clinics never build, and a patient complaint leaves you exposed.
| Tool | Reason to avoid for AU clinical data |
|---|---|
| Doximity Scribe | US verified physicians only. Not available to AU clinicians. |
| Abridge | Enterprise only US health systems. No AU procurement path. |
| Tali AI | Canadian data residency. Not AU available, privacy risk if used. |
| Lindy.ai Medical Scribe | US hosted, no Australian residency disclosure. |
| Suki AI | Available in AU but stores data in US. Heavy privacy paperwork required. |
| Microsoft Dragon Copilot | Not generally available in Australia as of 2026. |
| Smith.ai / Goodcall (clinical PII) | US resident receptionists, no AU residency disclosure for clinical work. |
Australian built scribes do not have this problem. Heidi Health, Lyrebird Health, PatientNotes, TeleScribe, i scribe and Telstra Health Smart Scribe all process and store data in Australia, Halaxy keeps its clinical suite onshore, and ShiftCare and Lumary run on Australian infrastructure. Choose any of these and your privacy paperwork is short; a US hosted vendor needs a much heavier compliance trail.
Who is responsible when AI gets it wrong in healthcare
Picking the right tool and confirming where the data lives still leaves one open question: who carries the can when the AI is wrong. AHPRA, the regulator for every registered health practitioner in Australia, has a clear position. You are personally responsible for any AI output that affects a patient record. The tool does not carry the liability. You do.
This applies to GPs, specialists, psychologists, physiotherapists, occupational therapists, nurses, pharmacists, dentists, optometrists and the other regulated professions. AHPRA expects you to understand the limits of the AI you use, to get informed patient consent that mentions AI, and to be ready to defend any clinical decision the AI influenced.
- Tell your insurer: your professional indemnity insurer needs to know what AI you are using, and the RACGP tells every GP to consult their indemnity provider before adopting any scribe.
- Expect questions at renewal: most insurers now ask which scribe, which storage region, what your written policy says and how you document patient consent. Using an offshore tool without telling your insurer may void your cover for an AI related claim. That is a five minute phone call to make before you trial anything.
Sources: AHPRA AI guidance and peak body positions (RACGP, APA, OTA, APS).
The Australian Physiotherapy Association, Occupational Therapy Australia, Speech Pathology Australia and the Australian Psychological Society take similar positions: the practitioner is accountable, transparency is mandatory, and choosing the tool is itself a clinical decision. Other regulated professions follow the same pattern, see our guides on AI tools for Australian lawyers and AI tools for Australian accountants.

When your staff use ChatGPT at the front desk
Accountability also applies to AI you did not officially adopt. Shadow AI is what happens when staff use personal AI tools, on personal accounts, to do clinic work, and it is the conversation Australian clinic owners are not having loudly enough. A receptionist pastes a referral letter into ChatGPT to summarise it.
A practice nurse uses Claude on a personal subscription to draft a letter to a specialist. Each is a privacy breach waiting to be found, and research suggests around 70 per cent of Australian small and medium businesses have this happening already. Meeting audio leaks the same way, since the free tiers of the main AI note takers keep transcripts offshore.
A workable policy answers three questions
- Which AI tools are approved for clinical work, and on which accounts
- Which are banned, and what happens if a staff member uses one
- How a staff member reports an AI concern without fear of penalty
- The effort: a Saturday morning of work for a two page policy, signed by every staff member and reviewed annually.
- The breach I see most: staff using personal ChatGPT to draft patient letters with the patient’s full name and date of birth in the prompt. A clinic approved ChatGPT Business account (formerly Team), properly configured removes that risk.
The verdict on shadow AI: staff are not breaking rules on purpose, they are being productive, and without a written policy they have no way to know that pasting patient information into a personal account breaks the Privacy Act. The fix is a two page policy naming the approved tools, the banned tools and how to raise a concern, signed by every staff member and reviewed annually.
What a pasted referral carries with it
An approved account decides which vendor gets the text, but a referral pasted at the front desk still carries the patient’s Medicare number and IHI to that vendor unless someone takes them out first. The NDIS Commission goes further for its sector: it expects “that no personal information of participants is disclosed to AI systems”.
Select the text, press one key, and Nonimo swaps the healthcare identifiers it recognises for placeholders on the provider’s own computer before anything reaches ChatGPT, Claude or Copilot, then restores them in the reply. Not a word of the note goes to Nonimo; a daily usage count does. See how an NDIS provider covers participant identifiers before pasting.
The front desk is also where new patient enquiries pile up, a job worth handing to AI on purpose. For aesthetic and cosmetic clinics, Podium Aesthetics AI replies across website chat, SMS, Instagram, Facebook and missed calls within seconds and books consultations into the clinic calendar, so a 9pm request does not wait until morning. Clinical advice stays with the practitioner.
Diagnostic imaging AI and TGA rules
Everything covered so far sits outside the Therapeutic Goods Administration’s medical device rules. Diagnostic imaging AI is the exception. Tools like Annalise.ai for radiology and Aidoc for emergency imaging are classified as Software as a Medical Device under the Therapeutic Goods Act, and they sit on the Australian Register of Therapeutic Goods (ARTG).
- Annalise at scale: its ARTG entry is 454945, and it is the most commonly deployed clinical AI across Australian radiology. I MED runs it across its network, and South Australian Medical Imaging deployed it across six metro and four regional hospitals.
- Why scribes are different: scribes and rostering AI produce draft notes or scheduling decisions that a clinician reviews, while Annalise produces a finding that influences a clinical decision directly. The TGA’s Digital Scribes guidance of February 2026 confirmed that ambient scribes generally sit outside the medical device framework when the clinician retains review responsibility.
Sources: TGA ARTG register and AU radiology deployments (I MED, South Australian Medical Imaging).
For most non imaging clinics this section is informational. If you refer to a radiology group that uses Annalise, you should know it and may mention it in your referral consent; if you buy point of care ultrasound with AI guidance, the TGA conversation becomes live. Cardiology is moving fast: the Baker Heart and Diabetes Institute’s AGILE Echo trial is deploying AI guided echocardiography across rural sites.

How to roll out AI in your clinic in 90 days
For everything except diagnostic AI, the clinics that get it right in 2026 will not be the ones that move fastest, but the ones that move in the right order. A clean 90 day rollout follows a predictable shape. If you are starting this month, the deadline lands inside it, so finish the paperwork phase before 10 December and let the rest follow.
- Weeks 1 to 2, paperwork: update your privacy policy for the December rules, draft the shadow AI staff policy, notify your indemnity insurer, and document the data flow for any AI tool already in use. It is the cheapest, highest leverage work, and almost nobody does it before deployment.
- Weeks 3 to 6, tool selection and pilot: pick one tool, ideally the cheapest compliant scribe for your system: Lyrebird Free for Best Practice, Smart Scribe with Heidi for MedicalDirector, Heidi or Medow for Gentu specialists, Heidi or PatientNotes for Cliniko allied health. Pilot with one or two clinicians, refine templates, document the consent script and verify the audit trail. No clinic wide rollout yet.
- Weeks 7 to 10, rollout and policy embedding: train every staff member on the approved tool, the banned tools list and the consent script, embed AI disclosure into intake forms, and publish the updated privacy policy live.
- Weeks 11 to 12, review: pull six weeks of scribe output, check accuracy against the original audio, review a sample of patient consents, and confirm the insurer has acknowledged the deployment in writing.
The 90 day rollout, phase by phase
Each row spans the same 12 week window, so bar position is the week the phase runs. Source: the rollout order set out in this section.
This is the work we do with healthcare clients at Aivy, an Australian AI automation agency. If you would like help, our AI consulting for Australian clinics and our healthcare and medical AI services pages are the entry point.
Frequently asked questions about AI in Australian healthcare
Are AI medical scribes legal in Australia?
Yes, AI scribes are legal in Australia as long as your clinic meets its Privacy Act obligations. You need informed patient consent, an updated privacy policy from 10 December 2026, and a documented data flow. The scribe is not the regulated party. You are.
What changes in December 2026 for my clinic?
From 10 December 2026, your privacy policy must disclose the kinds of personal information your software uses to make decisions that significantly affect patients, and the kinds of decisions it makes or substantially helps make. Health service providers do not get a turnover exemption. Penalties reach $66,000 per breach.
Is Heidi or Lyrebird better for Australian GPs?
It usually depends on which practice management system you use. Lyrebird is free for every Best Practice Premier customer through an official partnership. Heidi has ISO 27001 certification and stronger templates for complex Medicare items. Both store data in Australia.
Can I use ChatGPT with patient data in Australia?
Not on a personal consumer account. The free and Plus tiers of ChatGPT store data on US servers under terms that allow OpenAI staff to review it. A ChatGPT Business (formerly Team) or Enterprise account with data protection enabled, plus a documented privacy check, is the minimum for clinical use.
Does using an AI scribe affect my Medicare billing?
No. AI scribes are not prohibited for Medicare or telehealth billing. The standard rules still apply: both provider and patient must be in Australia, and the established relationship rule for telehealth applies. New telehealth patient end support items came into effect on 1 March 2026.
What does AHPRA say about AI in healthcare?
AHPRA holds every registered practitioner personally accountable for any AI output that affects a patient record. Patient consent must be informed, transparency is mandatory, and you must understand the limits of the tool. The position applies to every health profession.
Are AI scribes regulated as medical devices by the TGA?
Generally no. The TGA’s February 2026 guidance confirmed that ambient AI scribes sit outside the medical device framework when the clinician reviews and signs off on every output. Diagnostic imaging AI like Annalise.ai is regulated as a medical device and listed on the ARTG.
How do NDIS providers use AI for compliance audits?
NDIS providers use AI for rostering, evidence collection, restrictive practices reporting and incident management. Tools like Lumary, ShiftCare and SupportAbility attach NDIS Practice Standards to participant records and produce the audit trail the NDIS Commission expects.

The bottom line for Australian healthcare clinics in 2026
The Australian healthcare AI conversation in 2026 is no longer about whether you will use AI. It is about whether the AI you have already started using will survive 10 December. The clinics that win this year treat AI procurement as a compliance decision first and a productivity decision second, the opposite of how most clinics bought their first scribe.
A practical example from a Sydney clinic client earlier this year: four practitioners using three different scribes on personal accounts, no written policy, and a privacy policy last updated in 2021. In five weeks we landed one approved scribe (Lyrebird Free through BP Premier), a signed two page AI policy, an updated privacy policy and an insurer notification, for a Friday afternoon of partner time.
If you want help walking through the same exercise, the Aivy team works with Australian clinics, NDIS providers and allied health groups. We are Australian, honest about which tools we recommend, and we do not sell software: we sell the time it takes to do this properly. If that sounds useful, book a discovery call with the Aivy team.
Last updated: 19 October 2026